






Oral Steroids Compared: Dianabol, Anadrol, Anavar, Tbol & Winstrol

Few categories in performance pharmacology attract as much curiosity, and as much bad information, as oral steroids. A tablet looks harmless next to an ampoule, and that impression is where most mistakes begin. Dianabol, Anadrol, Anavar, Turinabol and Winstrol each carry decades of history, a distinct personality and clear reasons why experienced users choose them, along with costs the tablet format does nothing to soften.
This guide is written for the careful and conscious user: the adult who gets bloodwork before and after, involves a doctor, buys authentic product, sets realistic goals and treats every compound with respect. You will learn how oral anabolic steroids differ from injectables, what each compound is valued for, how they compare and what to monitor. Every compound here is a prescription-only medicine in most of Europe and prohibited in tested sport under the WADA code, and none of them is for beginners or teenagers.
Where we mention our RED line, the research-grade versions of the same molecules, be clear: Rogue’s RED-line orals are sold for research purposes only and are not for human consumption. You will not find doses or durations here; those are decisions for you and your doctor, based on your own health and blood results.
Key takeaways
- Oral steroids are 17-alpha-alkylated so they survive the liver’s first-pass metabolism, and that same modification is why every one of them places load on the liver.
- Short half-lives mean fast onset and fast clearance, but also sharper effects on HDL cholesterol and blood pressure than most injectables.
- Dianabol and Anadrol are the size-and-strength orals; Anavar, Turinabol and Winstrol are the dry orals, prized for strength and hardness without water.
- “Mild” is relative: even Anavar suppresses natural testosterone and lowers HDL cholesterol.
- The careful user gets baseline and follow-up bloodwork (liver enzymes, lipids, haematocrit, hormones), tracks blood pressure and keeps a doctor involved throughout.
- Orals are a tool for experienced adults, never a shortcut for beginners or anyone under 18, and they are banned in tested sport.
- Counterfeits are rampant, Anavar above all, so sealed, batch-coded, traceable product is non-negotiable.
What are oral steroids, and how do they differ from injectables?
Anabolic-androgenic steroids are synthetic derivatives of testosterone or its close relative dihydrotestosterone (DHT). They bind the androgen receptor in muscle and other tissues, increasing protein synthesis, nitrogen retention and, in most cases, red blood cell production. Injectable compounds, such as the esters in our guide to testosterone enanthate vs cypionate, are oil solutions that release slowly from a muscle depot over days; Testo Depot (Testosterone Enanthate) and the rest of our performance injectables work that way. Oral steroids work on a different principle.
17-alpha-alkylation: how a steroid survives being swallowed
Swallow unmodified testosterone and the liver breaks down almost all of it before it reaches the bloodstream: the first-pass effect. The solution, first applied in the 1930s with methyltestosterone, is to attach a methyl (or ethyl) group at the 17th carbon of the steroid skeleton. This 17-alpha-alkylation shields the molecule from the liver enzymes that would deactivate it, so a meaningful fraction reaches circulation intact. Every classic oral in this guide carries it.
Short half-lives, fast onset
Without an ester or a depot, oral steroids act quickly and clear quickly. Their half-lives are measured in hours rather than days, so blood levels peak within a few hours of a tablet and fall away within a day or so. Effects become noticeable within a short window, and the compound leaves the system soon after it is stopped.
The price: the liver does the heavy lifting
The alkylation that protects the molecule also slows the liver’s ability to process it, and a tablet arrives at the liver in concentrated form, straight from the gut. That is why oral anabolic steroids are associated with raised liver enzymes, impaired bile flow (cholestasis) and, with prolonged use, rarer but serious complications such as peliosis hepatis and liver tumours documented in the medical literature. Orals also increase the activity of hepatic lipase, which is why they depress HDL (“good”) cholesterol more sharply than injectable testosterone does.
Why careful users choose oral steroids
The experienced user does not reach for an oral because it seems easier than an injection, but for qualities injectables cannot easily replicate.
Speed and visible feedback
An oral begins working within days rather than weeks. Strength, training drive, recovery and muscular fullness can all move quickly, which is why orals have long been associated with giving a training phase early momentum or sharpening conditioning before a competition.
Control and quick clearance
Here short half-lives cut in your favour. If blood pressure climbs, a lipid panel deteriorates or mood changes, an oral is largely out of the system within days of stopping, while a long-ester injectable keeps acting for weeks. For the user who works with a doctor and monitors properly, that responsiveness is a genuine advantage.
No needles, and a precise character
Tablets need no injection and carry no risk of injection-site infection. Just as importantly, each oral has a sharply defined personality. Some aromatise and hold water, producing scale weight and fullness; others cannot aromatise and are prized for a dry, hard look and strength without extra bodyweight. Choosing between oral steroids is less about “stronger or weaker” and more about matching a molecule’s character to a goal.
A real clinical history
Several of these compounds were, and in some countries still are, licensed medicines: oxymetholone for certain anaemias, oxandrolone to support weight regain after surgery, trauma and severe burns, and stanozolol historically for hereditary angioedema. Their effects and risks are therefore reasonably well documented.
Dianabol and Anadrol: the size and strength orals
These two are the heavyweights: fast, potent and associated with rapid gains in bodyweight and strength. Both bring water along with tissue, and both demand the most respect where blood pressure and the liver are concerned.
Dianabol (methandienone): the original benchmark
Methandienone, also known as Dbol or methandrostenolone, was developed in the 1950s and became the first oral anabolic steroid in widespread athletic use. It is testosterone with a 17-alpha-methyl group and an extra double bond in the A-ring, giving it a high anabolic and moderate androgenic character. It does aromatise, converting to the potent oestrogen 17-alpha-methyloestradiol, and that explains both its appeal and its drawbacks.
Users value it for what it has always delivered: rapid strength on the big lifts, a full, pumped look, appetite, and drive in the gym. The honest caveat is that much of the early scale weight is water and glycogen, which does not stay once the compound is stopped. Water retention, raised blood pressure and a risk of gynaecomastia are a permanent part of the conversation, alongside liver strain, adverse lipid changes and suppression of natural testosterone.
Rogue stocks Dianabol 10 mg (Methandienone – Tablets), a sealed, batch-coded 100-tablet pack from European pharmaceutical manufacturing. For laboratories there is RED BOL (Methandienone 10 mg); methandienone’s long publication history makes it a standard reference compound in metabolite screening and detection-method validation.
Anadrol (oxymetholone): maximum oral power
Oxymetholone is a 17-alpha-alkylated DHT derivative with a 2-hydroxymethylene group on the A-ring. Introduced around 1960, it is still licensed in some countries for certain anaemias because it strongly stimulates red blood cell production, and its anabolic potency is among the highest of any oral. It is also a pharmacological puzzle: it binds the androgen receptor relatively weakly and cannot aromatise, yet produces marked oestrogenic-type effects, attributed to direct activity at the oestrogen receptor.
Experienced users choose it for dramatic gains in strength and size and an intense pump. That power is why it sits at the far end of the category. Oxymetholone is widely considered the most hepatotoxic oral in common use; it can raise blood pressure sharply, causes significant water retention, can push haematocrit (the share of your blood made up of red cells) upwards and strongly suppresses natural testosterone. It is for advanced users only, with baseline liver and lipid bloodwork, a doctor in the loop and a clear reason for choosing it over something milder.
It is available as Anadrol 50 mg (Oxymetholone – Tablets) and, for laboratory work, as RED A-DROL (Oxymetholone 25 mg), studied for the mismatch between its modest receptor binding and its pronounced functional activity.
Wet gains: what stays and what does not
Bloat is chemistry, not a flaw: oestrogenic activity and stored glycogen pull water into muscle and under the skin. Genuine tissue is built underneath, and how much you keep depends on training, nutrition and how well your own hormone production recovers.
Anavar, Turinabol and Winstrol: the dry orals
These three cannot convert to oestrogen. They are associated with strength without water, density and definition, which is why they are popular in cutting phases and in weight-class or speed-dependent sports where extra bodyweight is a cost. Each still carries the full set of 17-alpha-alkylated risks.
Anavar (oxandrolone): the mildest oral, with caveats
Oxandrolone, first synthesised in the early 1960s, is a DHT derivative in which a carbon atom in the A-ring is replaced by oxygen. That structure gives it a high anabolic and very low androgenic profile, and it does not aromatise at all. Clinically it has been prescribed to support weight restoration after major surgery, trauma and severe burns, and more of it is excreted unchanged than with other orals, part of why it is regarded as the best-tolerated compound in the category.
Users value it for lean, dry strength, a harder appearance and the preservation of muscle during a calorie deficit. But mild is relative, never absolute. Oxandrolone still loads the liver, is well documented for lowering HDL cholesterol, and does suppress natural testosterone; the belief that it does not is one of the most persistent myths in this field. For women, low androgenicity is not zero androgenicity: voice deepening and other virilising effects can occur and may be permanent.
Genuine oxandrolone is expensive to manufacture, which makes Anavar the most counterfeited of all oral steroids. Rogue supplies sealed, batch-coded Anavar 10 mg (Oxandrolone – Tablets) and the research-grade RED OXA (Oxandrolone 10 mg), a reference compound in research benchmarking anabolic-to-androgenic activity.
Turinabol (chlorodehydromethyltestosterone): steady, dry progress
Turinabol is methandienone with a chlorine atom added at the fourth carbon. That single change blocks aromatisation and dampens androgenic activity, turning Dianabol’s fast, wet profile into something slower, drier and more linear. Developed in East Germany in the 1960s, it became the backbone of that country’s state sport programme in the 1970s and 1980s.
Users choose Tbol for strength and muscle that accumulate steadily rather than in a spike, and that tend to stay visible because little of the change is water. It suits the athlete who values control over dramatic short-term numbers. The trade-offs are the familiar oral ones: liver strain, unfavourable lipid changes and suppression of natural hormone production. It is also a cautionary tale on detection, since the discovery of its long-lived metabolites led to a wave of retrospective positive tests on stored Olympic samples.
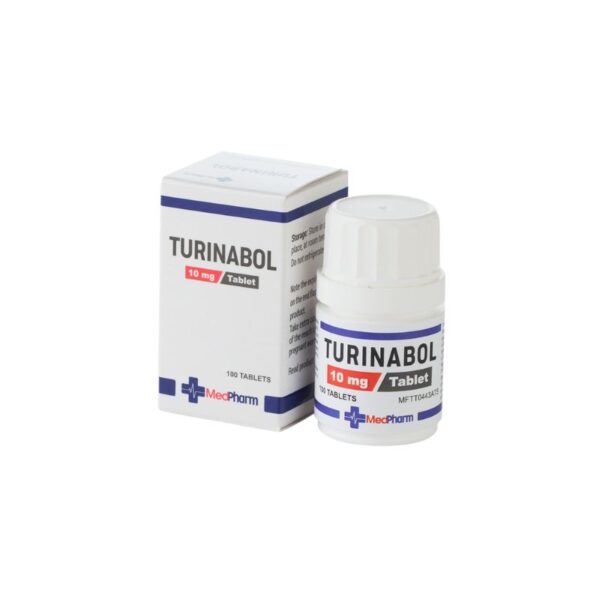
Rogue stocks Turinabol 10 mg (Chlorodehydromethyltestosterone – Tablets) and, for research, RED TURIX (4-Chlorodehydromethyltestosterone 10 mg), a fixture in mass-spectrometry method validation precisely because of those persistent metabolites.
Winstrol (stanozolol): definition and speed
Stanozolol, introduced in the early 1960s, is a DHT derivative with a pyrazole ring fused to the A-ring. That ring removes the structure aromatase needs, so it cannot become an oestrogen, and stanozolol is one of the few steroids that exists both as a tablet and as an injectable. It also lowers sex hormone-binding globulin (SHBG), raising the free fraction of other hormones in circulation.
Its reputation rests on the dry, sharply defined look that holds up on stage, and on strength and speed without added bodyweight. Its costs are equally well known: it is among the harder orals on the liver, it suppresses HDL cholesterol markedly, many users report joint discomfort attributed to its drying effect, and as a DHT derivative it can accelerate genetic hair loss.
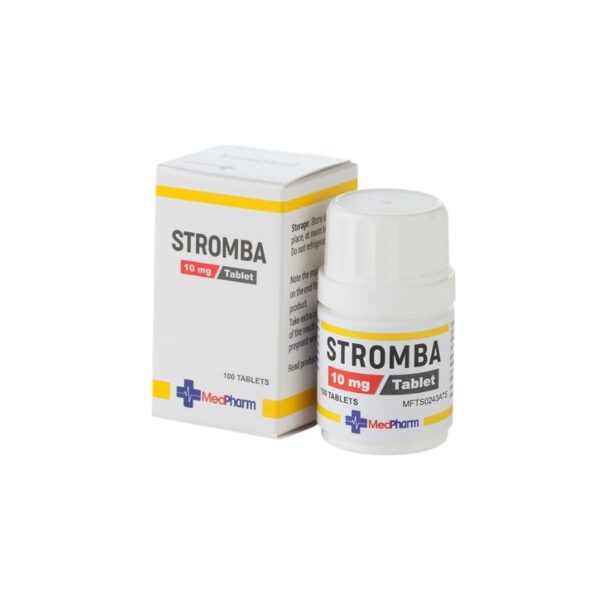
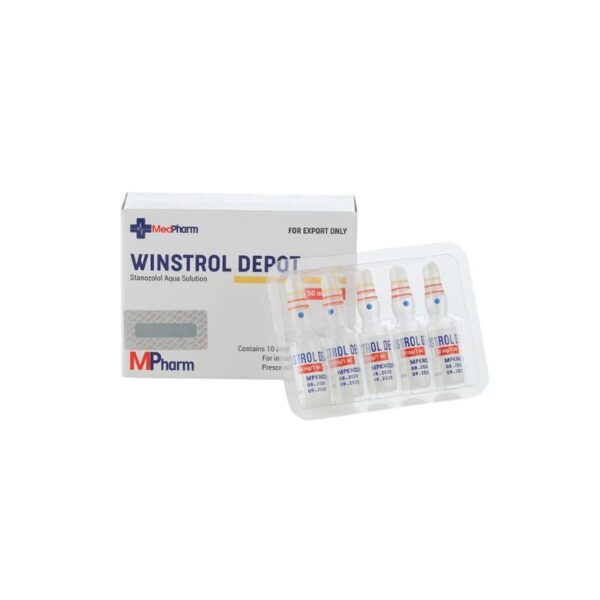
The oral form is available as Stromba 10 mg (Stanozolol – Tablets) and the research-grade RED STANOX (Stanozolol 10 mg). The injectable suspension is Winstrol Depot (Stanozolol – Injectable), with RED WIN (Stanozolol 50 mg/ml) as its research counterpart.
Oral steroids compared side by side
The table summarises each compound’s character. Half-lives are approximate figures commonly cited in the pharmacological literature, individual response varies, and none of it replaces a medical assessment.
| Compound | Derived from | Aromatises? | What users value it for | Approx. half-life | Liver and lipid load | At Rogue |
|---|---|---|---|---|---|---|
| Dianabol (methandienone) | Testosterone | Yes, to methyloestradiol | Rapid size, strength and fullness (wet) | About 3–6 hours | High; marked HDL drop; blood pressure rises with water retention | Dianabol 10 mg · RED BOL (research) |
| Anadrol (oxymetholone) | DHT | No, but oestrogenic-type effects | Maximum oral strength and mass (wet) | About 8–9 hours | Very high; strong lipid impact; raises haematocrit | Anadrol 50 mg · RED A-DROL (research) |
| Anavar (oxandrolone) | DHT | No | Lean, dry strength; muscle retention in a deficit | About 9–10 hours | Lowest of the group, but HDL suppression is well documented | Anavar 10 mg · RED OXA (research) |
| Turinabol (chlorodehydromethyltestosterone) | Methandienone | No | Steady, cumulative, dry gains | About 16 hours | Moderate to high; adverse lipid shift | Turinabol 10 mg · RED TURIX (research) |
| Winstrol (stanozolol, oral) | DHT | No | Definition, hardness, speed without bodyweight | About 9 hours | High; strong HDL suppression; joint dryness | Stromba 10 mg · RED STANOX (research) |
| Methyltrienolone | Trenbolone | No | Laboratory reference ligand only | Not well characterised in humans | Severe; never developed into a medicine | RED TRENO (research only) |
Methyltrienolone: the research-only outlier
RED TRENO (Methyltrienolone 1 mg) deserves its own note. Methyltrienolone, also called metribolone or R1881, is the 17-alpha-methylated form of trenbolone and one of the most potent androgens ever synthesised. Its liver toxicity was judged too severe for it to become a medicine, but its exceptionally tight androgen-receptor binding and negligible SHBG binding made its radiolabelled form the standard reference ligand in receptor-binding assays for decades. It is a laboratory benchmark, not a training compound. It is supplied strictly for research and is not for human consumption.
Choosing by goal, not by hype
Seen together, the logic is clear. Methandienone and oxymetholone deliver rapid size and strength and accept water as part of the deal. Oxandrolone, chlorodehydromethyltestosterone and stanozolol trade raw scale weight for dryness, density and control. No oral is easy on the body; they simply differ in how they spend your liver, lipid and blood-pressure budget. The careful user starts from the goal, asks which compound reaches it at the smallest physiological cost, and asks a doctor whether he or she is a candidate for any of them at all. You will find the sealed pharmaceutical tablets in our performance tablets category and the research-grade molecules in the RED orals collection, part of our wider research compounds line.
Side effects and risk management: what the careful user monitors
The benefits of oral steroids are real, and so are the risks. Responsible use is about measurement, not fear. These are the markers a doctor will typically check before, during and after any use of orals.
| Marker | Why it matters with orals |
|---|---|
| ALT, AST, GGT, bilirubin | Liver strain and impaired bile flow from 17-alpha-alkylation. Hard training can raise ALT and AST on its own, so GGT and bilirubin help a doctor read the picture. |
| HDL, LDL, triglycerides (ideally ApoB) | Orals depress HDL and raise LDL more sharply than injectable testosterone, shifting long-term cardiovascular risk. |
| Blood pressure | Water retention and vascular effects, most marked with Dianabol and Anadrol. Home readings add context between appointments. |
| Haemoglobin and haematocrit | Oxymetholone in particular stimulates red cell production; thicker blood strains the heart and raises clotting risk. |
| Testosterone (total and free), LH, FSH, SHBG, oestradiol | Documents suppression of your own hormone production and the wider hormonal picture. |
| Creatinine, eGFR, cystatin C | Kidney function; creatinine alone can mislead in muscular people. |
| Fasting glucose and HbA1c | Androgens can alter insulin sensitivity and glucose handling. |
Liver strain
Liver effects depend on the compound, the amount and the duration, and they accumulate across compounds: combining orals multiplies the load rather than adding to it. Yellowing of the skin or eyes, dark urine, pale stools, persistent itching or pain under the right ribs mean you stop and seek medical attention promptly.
Lipids, blood pressure and the heart
Lower HDL, higher LDL and raised blood pressure form the main long-term cardiovascular cost, and it is silent. You do not feel your lipid panel, which is exactly why the careful user tests rather than guesses, and why cardiovascular training, diet quality and sleep are not optional extras.
Suppression of natural testosterone
Every oral in this guide suppresses the hypothalamic–pituitary–testicular axis (HPTA). Oral-only use leaves the body producing less of its own testosterone, and recovery after stopping takes time and is not assured. Low libido, erectile difficulty, low mood and fatigue are a medical matter. Clinicians sometimes use licensed medicines such as Clomimed (Clomiphene 50 mg), found in our PCT category, to support recovery, but the choice, timing and dose belong to your doctor alone.
If sexual function changes, do not simply mask it. Erectile dysfunction medicines, from single-active tablets to combination formulas such as Black Triad (Combination Formula), sit in our sexual wellness range for a different purpose, and PDE5 inhibitors lower blood pressure while the orals above push it around: one more reason a doctor should see the whole picture. Our comparison of sildenafil vs tadalafil explains how that class works. Alkylated steroids can also intensify blood thinners such as warfarin, so every prescription you take needs to be on the table.
Oestrogenic, androgenic and other effects
Dianabol and Anadrol bring water retention and a risk of gynaecomastia. DHT-derived orals can worsen acne and accelerate genetic hair loss, stanozolol is linked to joint discomfort, and all androgens can affect mood, sleep and irritability. In women, virilising effects such as a deepening voice may not reverse.
Why a doctor belongs in the picture
A doctor screens you for conditions that make orals inappropriate (liver disease, high blood pressure, heart disease, lipid disorders or a strong family history), interprets your bloodwork in context, and recognises a problem early, while it is still easy to reverse. Dose and duration are set with that doctor, not copied from someone else’s log. That is the line between the conscious user and the gambler.
Why oral steroids are never a beginner shortcut
Orals are often presented as the entry-level option because they avoid needles. The opposite is true. Their liver and lipid costs are typically higher than those of injectable testosterone, they suppress natural production just the same, and for someone without a base they mask the lessons that matter most: how to train, eat and recover.
They are categorically not for teenagers. Androgens can close the growth plates early and permanently, and an adolescent endocrine system is still developing. Nobody under 18 should use them.
For adults, the foundation comes first: years of consistent, progressive training (start with how to structure your week for maximum muscle growth), proper recovery (why sleep is the most underrated supplement) and the patience to work through stalls (breaking through training plateaus). Only a lifter who has extracted most of what natural training can deliver has a coherent reason to consider pharmacology, starting with a doctor and a blood test. It is why we flag compounds like these in our Advanced level collection.
Then there is sport. Every compound here is on the WADA prohibited list, in and out of competition, and laboratories can detect some oral metabolites long after the compound has stopped acting. If you compete in a tested federation, oral steroids are off the table.
Why authenticity matters with oral steroids
Orals are among the most faked products in the performance market. Tablets are cheap to press and impossible to verify by eye. The common problems are underdosing, substitution (bargain “Anavar” is frequently a cheaper, harsher methylated steroid), contamination from unregulated production and inconsistent content from tablet to tablet. With a hepatotoxic compound, the wrong molecule is a different risk profile from the one you and your doctor agreed to, and your bloodwork means little if you do not know what produced it.
That is why Rogue’s position is simple:
- Sealed and EU-manufactured. Tablets such as genuine Anavar 10 mg and Stromba oral stanozolol come from Med Pharm and other European pharmaceutical manufacturing, in factory-sealed blisters and cartons.
- Traceable to the manufacturer. Batch-coded packaging you can check; never loose tablets, repackaging or grey-market stock.
- Batch-tested research line. RED orals such as RED OXA and RED TURIX are batch-tested and sold strictly for laboratory research.
- Discreet EU delivery. Plain, unbranded packaging with fast, tracked dispatch across the EU.
Authentic product does not make any compound harmless; it makes your doctor’s reading of your blood results rest on facts.
Frequently asked questions
Are oral steroids worse for your liver than injectable steroids?
Generally, yes. Oral steroids are 17-alpha-alkylated to survive first-pass metabolism, which loads the liver directly, whereas most injectables are not alkylated and bypass that first pass. Orals also depress HDL cholesterol more sharply, so liver enzymes and a lipid panel, reviewed by a doctor, are central to any oral use.
Which oral steroid is the mildest?
Oxandrolone (Anavar) has the gentlest reputation: low androgenic activity, no aromatisation and comparatively light handling by the liver. Mild is relative, though: it still suppresses natural testosterone, lowers HDL and loads the liver, and it is the most counterfeited oral of all.
Does Anavar shut down natural testosterone?
Yes. Like every anabolic steroid, oxandrolone suppresses the HPTA and therefore your own testosterone production. The degree varies, but the claim that it is non-suppressive is a myth, and recovery after stopping should be monitored by a doctor.
Dianabol vs Anadrol: which is stronger?
Oxymetholone (Anadrol) is generally regarded as the more potent and the harsher of the two, with greater liver strain and a stronger effect on blood pressure and haematocrit. Methandienone (Dianabol) is the classic benchmark: fast and effective, but aromatising, so water retention and oestrogenic effects are central to its profile. Both are for experienced adults only.
Do gains from oral steroids last?
Partly. With wet orals such as Dianabol and Anadrol, much of the rapid scale weight is water and glycogen that recedes after stopping. Dry orals such as Turinabol and Anavar produce slower changes that tend to hold better, but what you keep depends on training, nutrition and how well natural hormone production recovers.
Can oral steroids be detected in a drug test?
Yes. All the compounds in this guide are prohibited by WADA in and out of competition, and anti-doping laboratories now target long-lived metabolites. Turinabol’s long-term metabolites famously triggered retrospective positives on stored Olympic samples. If you compete in a tested sport, they are not an option.
Are oral steroids legal in Europe?
In most European countries, anabolic steroids are prescription-only medicines, and the rules on possession, import and supply differ from one country to the next. Check the law where you live. Prescription status exists because these medicines need medical supervision.
The bottom line on oral steroids
Oral steroids are among the most effective and most misunderstood compounds in performance pharmacology. Dianabol and Anadrol build size and strength fast; Anavar, Turinabol and Winstrol deliver dry, dense, controlled progress. Every one is 17-alpha-alkylated, suppresses natural testosterone and asks something of your liver, lipids and blood pressure. Used by an informed adult, with bloodwork, a doctor and authentic product, they are precision tools. Used casually, they are a fast route to problems.
Rogue’s RED-line orals are sold for research purposes only and are not for human consumption. When you are ready to compare authentic, sealed, EU-manufactured options, explore our Performance range and the full line-up of oral performance tablets.
This article is for educational purposes only and is not medical advice. Prescription medicines and performance compounds carry real risks; speak to a qualified doctor before using any of them, and never use them if you are under 18.
Products in this guide
-
 +34 Rogue Points
-
 +39 Rogue Points
-
 +34 Rogue Points
-
 +59 Rogue Points
-
 +74 Rogue Points
-
 +49 Rogue Points
-
 +79 Rogue Points
-
 +49 Rogue Points
-
 +59 Rogue Points
-
 +29 Rogue Points
-
 +44 Rogue Points
-
 +59 Rogue Points
Keep reading
 Performance Guides
 Performance Guides
 Performance Guides
